Abdominal wall reconstruction for large ventral abdominal hernia

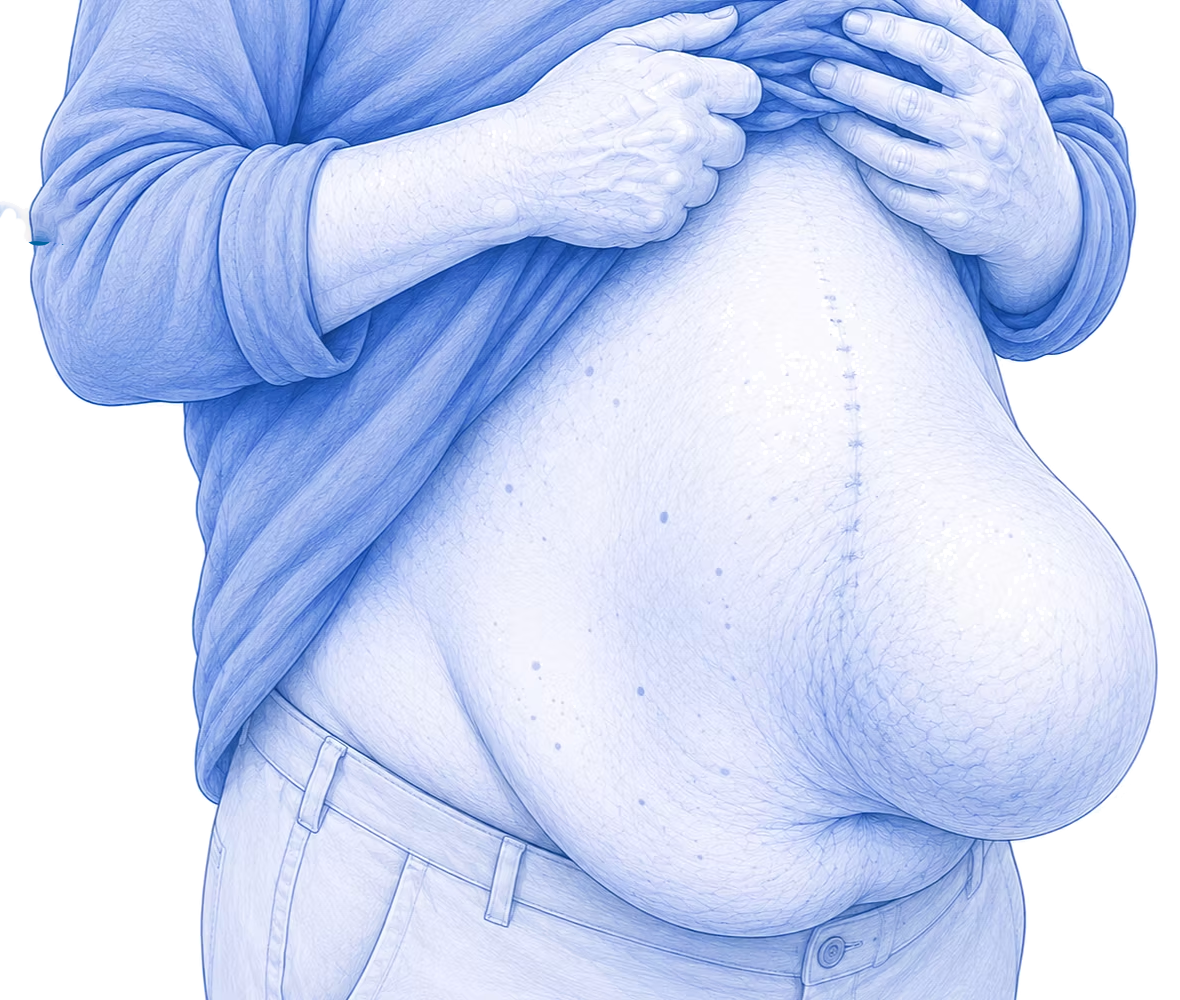
A giant ventral abdominal hernia is a large defect in the abdominal wall where abdominal contents, such as fat or bowel, protrude through a weakened area. It may occur after previous surgery, trauma, infection, obesity, pregnancy, or poor wound healing.

In very large hernias, the abdominal wall may no longer contain all the abdominal contents comfortably. This is sometimes called loss of domain. These hernias can cause pain, discomfort, skin problems, difficulty moving, bowel obstruction, and significant functional limitation.

Abdominal wall reconstruction is a complex operation to restore the strength and function of the abdominal wall.

What to expect

Before Your Surgery

  • Authorization should be obtained prior to surgery and will be done by the hospital or the rooms staff depending on whether you are an in- or outpatient.
  • Make sure that you have been fasting for solid foods for at least 6 hours prior to your surgery and for clear liquids or water for at least 2 hours prior to your surgery. Discuss your chronic medications with your doctor or hospital staff prior to your surgery as you usually are allowed to take chronic medications the day of surgery, barring diabetic medication the day of the procedure. If you are taking any blood thinning medication please discuss these in detail with your doctor as special arrangements need to be made for these.
  • Weight optimisation, smoking cessation, diabetic control, nutritional optimisation, blood tests, CT imaging, and anaesthetic assessment may be required before surgery.

Day of Surgery

You will be admitted to hospital and taken to theatre. After surgery, you may be monitored in recovery, high care, or ICU depending on the complexity of the operation and your medical condition.

You may have intravenous drips, a urinary catheter, wound drains, dressings, and an abdominal binder.

Procedure

The procedure is performed under general anaesthesia. It may be performed laparoscopically (in smaller cases) or open. Especially when large and complicated.

The hernia sac is opened, and the abdominal contents are carefully freed from scar tissue and returned to the abdominal cavity. The abdominal wall is then reconstructed using advanced techniques, which may include:

  • Release of abdominal wall muscle layers to allow closure without tension
  • Component separation
  • Placement of surgical mesh to reinforce the repair
  • Removal of excess or damaged skin if required
  • Drain placement to reduce fluid collection

The aim is to close the abdominal wall safely, restore function, and reduce the risk of recurrence.

Procedure Length

The procedure usually takes 3–6 hours, depending on the size of the hernia, previous surgeries, scar tissue, and complexity of the reconstruction.

Possible Complications

  • Possible complications include bleeding, infection, seroma or haematoma formation, wound breakdown, skin loss, mesh infection, bowel injury, bowel obstruction, respiratory complications, chronic pain, recurrence of the hernia, need for ICU care, and unintended damage to surrounding structures.

Duration of Hospital Stay

Hospital stay is usually 5–10 days, but may be longer in complex cases, especially if ICU care, wound care, or delayed bowel function occurs.

Discharge Instructions

  • Keep the wound clean and dry. Take prescribed pain medication, antibiotics, laxatives, or other medication as directed.
  • Wear the abdominal binder if advised. Avoid constipation, coughing without support, and straining. Monitor drains if discharged with them and follow instructions for drain care.
  • Please contact the rooms if you develop fever, worsening pain, wound redness, discharge, increasing swelling, vomiting, shortness of breath, or a recurrent bulge.

Return to Activities

  • Light walking is encouraged as soon as possible. Avoid heavy lifting, abdominal exercises, gym activity, and strenuous activity for at least 8–12 weeks.
  • Gradual return to activity will be guided by your surgeon.

Back to Work Estimation

  • Desk work: approximately 4–6 weeks.
    Physically demanding work: approximately 8–12 weeks or longer, depending on healing and the extent of reconstruction.

Follow-Up and Results Discussion

A follow-up appointment may be arranged 5–7 days after surgery for wound review and drain removal if necessary.

A further follow-up is usually arranged 10–14 days after surgery for wound assessment, suture or clip removal if required, and review of recovery progress. Histology discussion will occur if tissue was sent for analysis.